
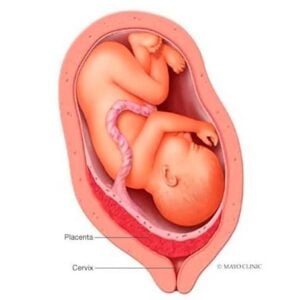
 Refers to the implantation of the placenta over the cervix.
Placenta previa is placental implantation directly over or very near the internal cervical os, classically presenting with painless vaginal bleeding in the second or third trimester.
A placenta whose edge is within 20 mm of the internal os is generally termed low-lying rather than true previa.
Occurs in 1 in 20 pregnancies.
3 types: marginal, with extension to the edge of the cervix, partial, with a portion of the placenta covering the cervix and complete where the cervical os is completely covered.
Usually present with painless vaginal bleeding during the third trimester.
Bleeding occurs as the lower third of the uterus stretches and thins in the third trimester with tearing at the margins.
As the cervix effaces and shortens in preparation of delivery, it shears off the vascular placental attachments above it , resulting in hemorrhage.
More common in women who have had children, are less then 20 years old, are older or smoke.
More common with large placentas.
Previous C-section or induced abortions may be associated with increased risk.
Associated with higher risk of congenital abnormalities.
Associated with increased risk of intrauterine growth restriction.
Diagnosis made at the time of bleeding or at the time of ultrasound examination.
Transvaginal ultrasonography (TVUS) is the diagnostic test of choice when placental location is uncertain or the placenta is low-lying on transabdominal imaging; it accurately measures the placental edge relative to the internal os and is not contraindicated when performed appropriately.
9 out of 10 cases found before 20 weeks gestation disappear as the placental position changes as the uterus grows.
Resolution is common when diagnosed earlier in pregnancy, so placental location should be reassessed later in gestation.
Treatment is immediate C-section or expectant management with bedrest and frequent monitoring until the newborn can survive outside the uterus.
Pelvic and rectal examinations are not to be done in PP unless staff is ready for emergency C-section.
May result in-life-threatening hemorrhage.
Associated with increased risk of postpartum hemorrhage.
Increased risk of placenta accreta.
Prior cesarean delivery, particularly with an anterior previa, should prompt evaluation for placenta accreta spectrum (PAS) because the combination increases the risk of severe hemorrhage and hysterectomy.
Management:
Clinical Guidelines recommend planned cesarean delivery at 36 0/7 to 37 6/7 weeks for stable patients with placenta previa without bleeding or other obstetric complications; active hemorrhage requires delivery based on maternal and fetal status, without delaying for corticosteroid administration.
Stable patients without bleeding may be managed as outpatients when rapid access to hospital care and individualized counseling are available.
Any bleeding, contractions, pain, or fluid loss warrants immediate hospital assessment; symptomatic or recurrently bleeding patients generally require inpatient care and corticosteroids when preterm delivery is likely.
Delivery should occur in a unit with obstetric anesthesia, neonatal support, and immediate blood-bank capability; suspected PAS requires a multidisciplinary specialist center.
Clinical takeaway: The next step for suspected placenta previa is TVUS to define the internal-os relationship and assess for PAS, while any active bleeding is an obstetric emergency; stable uncomplicated previa is generally delivered by planned cesarean at approximately 36–37 weeks.