
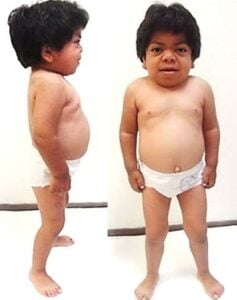
 Mucopolysaccharidoses II (MPS II, Hunter syndrome) is a rare, X-linked recessive lysosomal storage disorder caused by pathogenic variants in the IDS gene, which encodes the enzyme iduronate-2-sulfatase (I2S) located on chromosome Xq28.
Itis a rare, inherited lysosomal storage disorder.
It is caused by a deficiency of the enzyme iduronate-2-sulfatase (I2S).
The deficiency or absence of I2S the enzyme iduronate-2-sulfatase (I2S)impairs the lysosomal degradation of the glycosaminoglycans (GAGs) heparan sulfate and dermatan sulfate, resulting in their progressive accumulation within lysosomes of virtually all cell types.
Under physiological conditions, I2S catalyzes the hydrolysis of the 2-sulfate group from iduronic acid residues in heparan sulfate and dermatan sulfate, which is a critical step in their lysosomal degradation.
This accumulation leads to lysosomal hypertrophy, increased lysosome numbers, and widespread cellular dysfunction, affecting cell adhesion, endocytosis, intracellular trafficking, ionic balance, and inflammatory responses.
This deficiency leads to a harmful buildup of complex sugar molecules called glycosaminoglycans (GAGs) in cells, tissues, and organs throughout the body.
The spectrum of IDS mutations is broad, including missense, nonsense, splice-site mutations, small insertions/deletions, and complex rearrangements.
Missense mutations are most frequent, but large deletions and complex rearrangements are associated with more severe phenotypes.
More than 500 different mutations have been described, including missense, nonsense, splice-site mutations, small insertions/deletions, and large gene rearrangements.
The disorder primarily affects males, with rare symptomatic females due to skewed X-inactivation or chromosomal abnormalities.
In MPS II, absent or markedly reduced I2S activity leads to the progressive accumulation of partially degraded glycosaminoglycans (GAGs), specifically heparan sulfate and dermatan sulfate, within lysosomes of virtually all cell types.
This accumulation results in lysosomal hypertrophy, impaired autophagic flux, altered intracellular trafficking, and secondary disruption of cellular homeostasis.
The buildup of GAGs also interferes with the function of other lysosomal proteins and enzymes, further exacerbating cellular dysfunction.
In the pathogenesis of MPS II, there are altered antioxidant responses in the brain, downregulation of autophagic processes, suppression of sulfur catabolism, and immune dysregulation in the liver: suggests that the disease process extends beyond simple substrate accumulation and involves secondary cellular and molecular perturbations.
Missense mutations account for approximately 30% of cases and are associated with a spectrum of disease severity, ranging from severe neuronopathic forms to attenuated phenotypes with minimal CNS involvement.
Mutations causing severe disease tend to induce greater conformational changes in the enzyme, leading to more profound loss of function, whereas mutations associated with attenuated disease result in milder structural perturbations.
Large deletions, nonsense mutations, and certain splice-site mutations typically result in complete absence of enzyme activity and are more frequently associated with the severe, neuronopathic phenotype.
Familial studies have shown
Individuals with the same IDS mutation generally exhibit similar clinical phenotypes, but considerable heterogeneity exists, suggesting additional genetic, epigenetic, or environmental factors.
The ratio and sulfation pattern of accumulated GAGs also influences disease manifestations.
In MPS II, heparan sulfate predominates over dermatan sulfate, and the degree of sulfation is higher compared to MPS I.
This biochemical distinction underlies differences in clinical features between MPS I and II, such as the absence of corneal clouding in MPS II and the greater propensity for neurological involvement due to the role of heparan sulfate in neuronal development.
MPS II is a multisystem, progressive disorder with a broad spectrum of severity, ranging from severe, rapidly progressive neuronopathic forms to attenuated, slowly progressive non-neuronopathic forms.
The onset of symptoms is typically between 1.5 and 4 years of age.
Infants are asymptomatic and have normal growth parameters at birth.
The earliest signs often include coarsening of facial features, macroglossia, prominent supraorbital ridges, a broad nose and nasal bridge, large rounded cheeks, and thick lips.
Macrocephaly is universal and may be accompanied by communicating hydrocephalus.
Musculoskeletal involvement is prominent, with joint stiffness, contractures, and generalized thickening and abnormal modeling of long bones, especially the ribs.
Gait abnormalities, kyphosis, and scoliosis develop early, with kyphosis present in up to half of children under 10 years with the neuronopathic form.
Growth is typically normal until about age 5, after which growth velocity slows, resulting in short stature.
Carpal tunnel syndrome is common, even in young children, and spinal stenosis may develop, leading to neurologic compromise.
Hepatosplenomegaly is nearly universal, and hernias of umbilical and inguinal type are frequent, often requiring surgical repair in early childhood.
Cardiac involvement is a major source of morbidity and mortality, with the majority of patients developing valvular heart disease, most commonly affecting the mitral, aortic, tricuspid, and pulmonary valves, with associated murmurs, ventricular hypertrophy, and hypertension.
Cardiac failure and obstructive airway disease are leading causes of death.
Respiratory manifestations are significant and progressive.
Airway narrowing results from GAG deposition in the tongue, oropharynx, and trachea.
It compounded by thickened secretions, chest wall stiffness, and hepatosplenomegaly, which reduces thoracic volume and leads to frequent upper respiratory infections, sleep apnea, and ultimately airway obstruction requiring positive pressure support or tracheostomy.
Hearing loss, both conductive and sensorineural,
Often hearing loss is accompanied by recurrent otitis media.
Ocular involvement is less prominent than in MPS I; corneal clouding is rare and, if present, only detectable by slit-lamp examination.
Neurologic involvement distinguishes the two major phenotypes.
In the neuronopathic form, progressive cognitive decline begins in early childhood, typically between ages 6 and 8:with developmental regression, behavioral difficulties, and, in some cases, seizure disorders.
The non-neuronopathic form is characterized by normal or near-normal intelligence, though learning disabilities may be present.
Cervical spinal cord compression with spastic paresis may occur in older patients with the attenuated form.
The natural history of MPS II relates to the degree of CNS involvement and the rate of progression of somatic disease.
In the severe, neuronopathic form, children develop cognitive impairment and behavioral disturbances, with loss of acquired skills and progressive neurologic deterioration.
Death typically occurs in the first or second decade of life, most often due to respiratory failure or cardiac disease.
Individuals with the attenuated, non-neuronopathic form may survive into adulthood, sometimes into the fifth or sixth decade, with normal intelligence but significant somatic disease burden.
The diagnosis of MPS II is based on a combination of clinical suspicion, biochemical testing, and molecular genetic confirmation.
Diagnosis requires the demonstration of absent or markedly reduced I2S enzyme activity in relevant tissues (leukocytes, fibroblasts, or plasma) in a male proband, with normal activity of at least one other sulfatase to exclude multiple sulfatase deficiency.
Alternatively, theidentification of a hemizygous pathogenic variant in the IDS gene by molecular genetic testing is diagnostic.
In females, who are rarely affected, diagnosis is established by identification of a heterozygous pathogenic IDS variant in the context of suggestive clinical features.
The recommended diagnostic workflow begins with clinical suspicion based on characteristic features such as coarse facial features, hepatosplenomegaly, skeletal abnormalities, developmental delay, and cardiac involvement.
The condition is divided into two primary forms:
Severe (Neuropathic) Form: Involves progressive cognitive decline and developmental regression around ages 4 to 8, with a shortened life expectancy typically into the second decade of life.
Attenuated (Non-Neuropathic) Form: Intelligence is unaffected, and individuals can survive into adulthood.
Initial laboratory evaluation includes urinary glycosaminoglycans quantification and fractionation.
Quantitative assays, such as the dimethylmethylene blue (DMB) dye-binding assay, are used to measure total urinary GAGs
Qualitative or semi-quantitative fractionation methods, including agarose or polyacrylamide gel electrophoresis and thin-layer chromatography, help identify the specific GAG species elevated in MPS II.
Advanced mass spectrometry-based assays enable precise quantification and fractionation of GAG-derived disaccharides, improving diagnostic accuracy and allowing for unambiguous subtyping of MPS and related disorders.
The cornerstone of laboratory diagnosis is the quantitative measurement of I2S enzyme activity, typically performed in leukocytes, cultured fibroblasts, or plasma.
Most affected males have undetectable or severely reduced I2S activity.
Molecular confirmation is recommended for all patients with biochemical evidence of MPS II.
Newborn screening for MPS II has been implemented in the United States, with measurement of I2S activity in dried blood spots.
Abnormal results are followed by confirmatory testing, including repeat enzyme assays, urinary GAG analysis, and molecular genetic testing.
The two-tiered approach—first-tier enzymatic assay followed by second-tier GAG analysis—has been shown to reduce false positive rates to near zero, especially when advanced mass spectrometry methods are employed.
MPS II in newborn screening reflects the growing evidence that early diagnosis and presymptomatic treatment improve clinical outcomes.
Differential Diagnosis:
The clinical presentation of MPS II overlaps significantly with other mucopolysaccharidoses (MPS), mucolipidoses, and related lysosomal storage disorders.
The principal conditions in the differential diagnosis of MPS II include MPS I (Hurler syndrome), MPS III (Sanfilippo syndrome), MPS IV (Morquio syndrome), MPS VI (Maroteaux-Lamy syndrome), MPS VII (Sly syndrome), multiple sulfatase deficiency (MSD), mucolipidosis II and III (ML II/III), and other lysosomal storage disorders such as alpha-mannosidosis, fucosidosis, and sialidosis.
MPS I is autosomal recessive and caused by alpha-L-iduronidase deficiency.
MPS I shares many somatic features with MPS II, but is distinguished by the presence of corneal clouding, which is absent in MPS II.
MSIII is characterized by severe central nervous system degeneration and behavioral abnormalities, with relatively mild somatic involvement.
MPS IV presents with short stature, chest deformity, and severe skeletal dysplasia, but normal intelligence and corneal clouding.
MPS VI is similar to MPS I and II in somatic features but is autosomal recessive and caused by arylsulfatase B deficiency, with corneal clouding and rare neurocognitive involvement.
MPS VII is autosomal recessive and caused by beta-glucuronidase deficiency, often associated with non-immune hydrops fetalis.
MSD is autosomal recessive and results from deficiency of formylglycine-generating enzyme, leading to low activity of multiple sulfatases.
Clinically, MSD can mimic MPS II, but is distinguished by low activity of at least two sulfatase enzymes.
ML II/III are autosomal recessive disorders caused by defects in lysosomal enzyme targeting, presenting with coarse facies, dysostosis multiplex, joint stiffness, and organomegaly, but distinguished by elevated activity of multiple lysosomal hydrolases in plasma.
Common Physical Signs: Coarse facial features, enlarged head (macrocephaly), a deep hoarse voice, umbilical or inguinal hernias, enlarged liver and spleen (hepatosplenomegaly), airway obstruction, and joint stiffness.
Genetic Mutation: Caused by changes or mutations in the IDS gene.
Inheritance Pattern: Follows an X-linked recessive pattern, meaning it affects almost exclusively males because they have only one X chromosome.
Treatment and Management Strategies
Treatment: Primarily involves weekly intravenous enzyme replacement therapy (ERT) with recombinant idursulfase to help manage physical symptoms and improve endurance, though standard ERT does not cross the blood-brain barrier to treat neurological symptoms.
Supportive and palliative care address airway, cardiac, and joint complications.
Intravenous enzyme replacement therapy, ameliorates systemic manifestation of MPSII but it fails to prevent neurocognitive decline owing to limited penetration of the blood brain barrier.
Tividenofusp alpha a fusion iduronate 2 sulfatase with a transferrin receptor binding domain overcomes this limitation and enables enzymes delivery to both brain and peripheral tissues.
Tividenofusp alpha reduces sustained reductions in CSF and urinary heparan sulfate levels to near normal values as well as decreased serum neurofilament light chain levels, indicating preserved neuronal integrity.
The study demonstrated that tividenofusp alfa was associated with frequent infusion-related adverse events, most commonly pyrexia, urticaria, and vomiting, despite routine premedication. Importantly, cerebrospinal fluid heparan sulfate levels were reduced by 91% and urinary heparan sulfate by 88% from baseline, with reductions maintained through week 153.
Cognitive adaptive function, stabilized, or improved with this agent.
The cornerstone of MPS II management is enzyme replacement therapy (ERT) with recombinant iduronate-2-sulfatase (idursulfase, Elaprase®).
The recommended dosage is 0.5 mg/kg administered as a weekly intravenous infusion.
This regimen has demonstrated efficacy in improving functional capacity (as measured by the six-minute walk test, increasing forced vital capacity, reducing hepatosplenomegaly, and decreasing urinary GAG excretion.
ERT prolongs survival and improves somatic symptoms across age groups, including infants and older children.
The benefits are most pronounced when therapy is initiated early in the disease course, before irreversible organ damage occurs.
ERT is generally well tolerated, but infusion-related reactions (e.g., fever, rash, hypotension) may occur.
Ongoing monitoring for infusion reactions and antibody development is recommended.
These are typically managed with premedication using antihistamines or corticosteroids.
Development of anti-idursulfase antibodies is observed in a subset of patients.
Supportive and symptom-directed management is essential
Key supportive interventions include management of airway obstruction (tonsillectomy, adenoidectomy, tracheostomy, CPAP), aggressive treatment of recurrent ear infections and hearing loss (pressure-equalizing tubes, hearing aids), orthopedic interventions for joint contractures and carpal tunnel syndrome (surgery, physiotherapy), cardiovascular management per cardiology guidelines (medical therapy, valve replacement), neurosurgical interventions for hydrocephalus and spinal stenosis, ophthalmologic care, developmental and behavioral support, and management of sleep disturbances.
Hematopoietic stem cell transplantation (HSCT) has been explored as a potential therapy for MPS II, but controlled studies are lacking, and outcomes in severe forms have been disappointing, with progressive cognitive decline despite transplantation.
HSCT is not considered a standard or acceptable treatment modality for MPS II at present, except in rare, highly selected cases or research settings.
Emerging CNS-Targeted and Gene Therapies
Given the limitations of ERT, particularly its inability to address CNS involvement, several novel therapeutic strategies are under investigation.
CNS-targeted therapy is tividenofusp alfa, a fusion protein comprising iduronate-2-sulfatase linked to an engineered transferrin receptor–binding Fc domain.
This design enables the enzyme to utilize receptor-mediated transcytosis across the blood-brain barrier, achieving CNS exposure after intravenous administration.
In a multicenter phase 1–2 study, weekly intravenous tividenofusp alfa was administered to 47 male patients with MPS II, aged up to 18 years, over a 24-week primary analysis period, followed by long-term extension phases.
Adaptive behavior stabilized or improved, and liver volumes normalized or remained normal.
Alternative strategies for direct CNS delivery of IDS include intrathecal and intracerebroventricular administration of ERT, as well as fusion proteins such as pabinafusp alfa, which links idursulfase to an anti-human transferrin receptor antibody.
Ex vivo hematopoietic stem cell gene therapy (HSCGT) and in vivo adeno-associated viral (AAV) vector–mediated approaches are also advancing. HSCGT with IDS.
ApoEII fusion has demonstrated sustained IDS activity in the brain and peripheral organs, clearance of storage material, correction of neuroinflammation, and prevention of neurodegeneration for up to 16 months post-treatment in murine models, with no observed toxicity.
In vivo gene therapy using AAV vectors has achieved 89% of wild-type IDS activity in the brain and complete correction of neuropathology in MPS II mice.
The prognosis and long-term outlook for patients with MPS II are determined by the presence or absence of CNS involvement, the timing of diagnosis, and the availability of disease-modifying therapies.
Symptoms typically do not appear at birth, becoming noticeable between ages 2 and 4.
Most patients with the severe (neuronopathic) form die before age 20, and those with the attenuated form surviving into their third, fourth, or even fifth decade.
The introduction of ERT with intravenous idursulfase has significantly altered the natural history of the disease.
ERT is associated with a substantial increase in survival.
Specifically, median survival in ERT-treated patients is reported at 33 years, compared to 21 years in untreated patients, representing a median increase in survival of approximately 10–12 years and a 54–58% reduction in mortality risk.
ERT primarily addresses somatic manifestations and does not cross the blood-brain barrier, thus offering limited benefit for CNS symptoms.
The prognosis for patients with neuronopathic MPS II remains guarded, with progressive neurocognitive decline and early mortality despite ERT.
In contrast, patients with non-neuronopathic MPS II derive greater benefit from ERT, with improved functional capacity, reduced organomegaly, and increased life expectancy.
Adult survivors of MPS II, particularly those with the attenuated phenotype, continue to experience significant disease burden.
Adult patients require ongoing multidisciplinary management, with high rates of surgical interventions (e.g., hernia repair), hearing aid use, and persistent cardiovascular and respiratory complications.
The median six-minute walk test distance in treated adults is 436 meters, reflecting moderate impairment in functional capacity.
Cardiovascular involvement, including valvular disease and left ventricular hypertrophy, is common and contributes to morbidity.
Airway obstruction and oxygen dependency, are frequent and remain a leading cause of mortality.
Quality of life in adulthood is often compromised by progressive musculoskeletal, cardiac, and respiratory manifestations, despite ERT.
Limitations of current therapies-inability to address CNS manifestations, life-long treatment burden, lack of standardized transition from pediatric to adult care, inadequate pain management, and insufficient psychosocial and educational support.
In summary, MPS II is a rare, X-linked lysosomal storage disorder with a complex pathophysiology, broad clinical spectrum, and significant long-term disease burden.
Early diagnosis, prompt initiation of ERT, and comprehensive multidisciplinary management are essential for optimizing outcomes.
Emerging CNS-targeted and gene therapies hold promise for addressing the major unmet need of neurocognitive decline in neuronopathic MPS II.
Diagnosis: Confirmed via urine GAG screening followed by an enzymatic assay measuring I2S activity in leukocytes or blood, alongside genetic testing.