
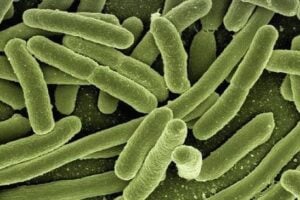
 Clostridium botulinum is a Gram-positive, rod-shaped, anaerobic (oxygen-avoiding), spore-forming bacterium commonly found in soil, marine sediments, and dust worldwide.
It produces botulinum neurotoxin (BoNT), one of the most potent toxins known, which causes botulism — a rare but potentially life-threatening neuroparalytic illness.
The botulinum bacteria exist mostly as hardy spores that survive harsh conditions for years.
Under low-oxygen, low-acid (pH >4.6), and warm conditions such as improperly canned or preserved food, the spores germinate, grow, and release the toxin.
The toxin itself is heat-labile and can be destroyed by boiling for 10 minutes but the spores require higher heat/pressure to kill.
Types of Botulism
There are five main forms:
Foodborne botulism: From eating food with pre-formed toxin: home-canned low-acid foods like vegetables, meats, or fish.
Symptoms start 12–36 hours (range: 4 hours–8 days) after ingestion.
Infant botulism: Most common in the U.S. making up about 70% of cases.
Spores from honey or dust colonize an infant’s immature gut and produce toxin in the intestines.
Affects babies under 12 months.
Recent multistate outbreaks linked to contaminated powdered infant formula.
Wound botulism: Spores enter a wound (injection sites in drug users or deep cuts) and produce toxin there.
Adult intestinal toxemia by colonization:Rare; similar to infant form but in adults with gut issues.
Iatrogenic botulism: From excessive or improper medical/cosmetic use of botulinum toxin injections.
Botulism is not contagious person-to-person.
The toxin blocks acetylcholine release at neuromuscular junctions, causing descending flaccid paralysis-symmetric, starting with cranial nerves and moving downward.
No fever, and consciousness remains intact.
Common early signs (foodborne/infant similar but infants show constipation, poor feeding, weak cry, floppy appearance:
Blurred/double vision, drooping eyelids (ptosis)
Dry mouth, difficulty swallowing/speaking (dysarthria, dysphagia)
Facial weakness
Descending muscle weakness → arms, legs, respiratory muscles
Breathing difficulty that can lead to respiratory failure
Gastrointestinal symptoms (nausea, vomiting, abdominal pain, diarrhea/constipation) may precede neurological ones in foodborne cases.
Untreated, it can cause death from respiratory failure.
Diagnosis and Treatment Diagnosis is clinical (symptoms + history) plus lab confirmation (toxin detection in serum/stool/food or culture of the organism) via public health labs.
Treatment:
Immediate botulinum antitoxin (e.g., heptavalent for adults; BabyBIG for infants) to neutralize circulating toxin
Treatment most effective when applied early.
Supportive care: Hospitalization, often ICU with mechanical ventilation if breathing is affected.
Wound debridement/antibiotics for wound botulism, but antibiotics are not routinely used for foodborne/infant as they may worsen toxin release.
Full recovery can take weeks to months with supportive care; mortality is low (5–10%) with prompt treatment.
Prevention Food safety: Use pressure canning (not water-bath) for low-acid foods.
Boil home-canned foods 10+ minutes before eating.
Avoid bulging/dented cans or off-smelling preserved foods.
Refrigerate oils with garlic/herbs and baked potatoes promptly.
Infants: Never give honey or corn syrup to babies under 1 year.
Avoid homemade or unpasteurized products.
Proper wound care; avoid injecting black-tar heroin linked to wound botulism.
Commercial canning is highly regulated and very safe.
Medical Uses of Botulinum Toxin
The toxin is FDA-approved and widely used therapeutically:
Cosmetic: Reduce facial wrinkles
Medical: Chronic migraines, cervical dystonia, blepharospasm, spasticity post-stroke, hyperhidrosis, overactive bladder, strabismus, and more.
Effects last ~3 months; side effects are usually mild when administered properly.